4.9★★★★★142 Google reviews
Doncaster clients rate us 4.9
142 Google reviews with an average of 4.9 stars. Read what clients say about their treatment and our follow-up.
Read our Google reviewsBrown marks, red marks and pitted texture look like one problem in the mirror and behave like three in practice. Two of them fade on their own with the right protection. The third does not, and needs work that rebuilds collagen over months. We tell you which you have before you spend anything, because the answer changes the plan, the timeline and the price.
Start with a £30 AI skin analysis. It names every scar and mark on your skin before anything is priced, and it is completely free when you go ahead with any treatment.
Real Google reviews from Dermacy Clinic clients. Every plan here starts with an assessment and is reviewed against your own first images.
142 Google reviews with an average of 4.9 stars. Read what clients say about their treatment and our follow-up.
Read our Google reviewsI recently had the Fire & Ice facial and oh my god I honestly couldn’t be happier with the results. I have very sensitive, acne-prone skin, so I’m always nervous about trying new treatments, but this facial was amazing from start to finish.
It was my first time at the clinic where I had a is clinical facial. Nebahat was so warm, welcoming and very professional. The skin analysis was grest and she really took the time to look at my skin in great detail and gave brilliant advice and recommendations. I will definitely be making a second appointment.
This single distinction decides whether you need a course of treatment or mainly patience and sunscreen.
Press a clear glass gently against the mark and look: redness that disappears under pressure is a vessel problem, colour that stays is pigment, and a dent that is still visible either way is texture.
Brown or grey-brown flat marks. Not a scar.
Pink, red or purple flat marks. Also not a scar.
Pits, dents and uneven texture.
Hypertrophic and keloid. A different condition.
Most people arriving here with “acne scars” have a mixture, usually weighted towards marks rather than texture. That is good news and it is worth knowing before you buy a course of anything.
Book your skin consultationAtrophic scars come in three shapes and they do not respond equally. Any clinic offering one treatment for all of them is selling a device rather than treating a scar.
Broad, shallow, wave-like dips with sloping edges. The skin looks uneven in side light rather than pitted.
Collagen remodelling. These respond best of the three to needling and resurfacing work.
Round or oval depressions with defined edges, like a shallow crater.
Repeated collagen remodelling. Slower than rolling, and improvement rather than removal.
The same shape but steep-walled and clearly set into the skin.
Usually needs procedures beyond resurfacing — the walls have to be released or excised.
Narrow and deep, like a pinprick that goes down rather than across.
Focal techniques that treat the scar individually. Needling and peels largely pass over them.
Raised, firm, sometimes itchy or tender. Chest, shoulders and jawline.
A medical pathway. Resurfacing is the wrong direction and can worsen them.
Most faces carry more than one type. The plan is built around the mix you actually have, and the parts we cannot treat here are named at the assessment rather than quietly left out.
Book your skin consultationScarring is treated by making the skin build new collagen, repeatedly, over months. There is no version of this that works in one visit.
What changes between plans is the depth, the spacing and what supports it at home.

iS Clinical, Medik8 and mesoestetic at our Armthorpe clinic.
Nothing scar-related starts while spots are still forming. New inflammation makes new marks, so treating scars underneath active acne is paying to chase a moving target. If your acne is still active, that gets sorted first — see acne treatment.
Controlled micro-injury that triggers collagen remodelling, spaced four to six weeks apart and judged as a course rather than a session. This is the core of what improves rolling and shallow boxcar scarring. See microneedling.
Used where congestion, surface texture and post-acne pigment are part of the picture, and stepped down for deeper skin tones. See chemical peels.
Matched to your skin at the assessment, with the in-clinic step and the homecare taken from one system rather than assembled from whatever is on the shelf.
Broad-spectrum SPF 50 every day. UV darkens post-acne marks faster than any treatment can lift them, and it is the single most common reason a good plan underperforms.
Scarring changes slowly enough that memory is unreliable. Images at the start and at review are how you actually know whether it worked.
The plan and its full cost are agreed and written down at your assessment, before anything is booked — the in-clinic sessions, the homecare and the number of weeks, together.
The core of the texture work for rolling and shallow boxcar scarring, judged three to six months after the last session.
For surface texture, congestion and post-acne marks, alongside needling rather than instead of it.
We image your skin, separate marks from true scarring and name every scar type before anything is priced. It is completely free when you go ahead with any treatment.
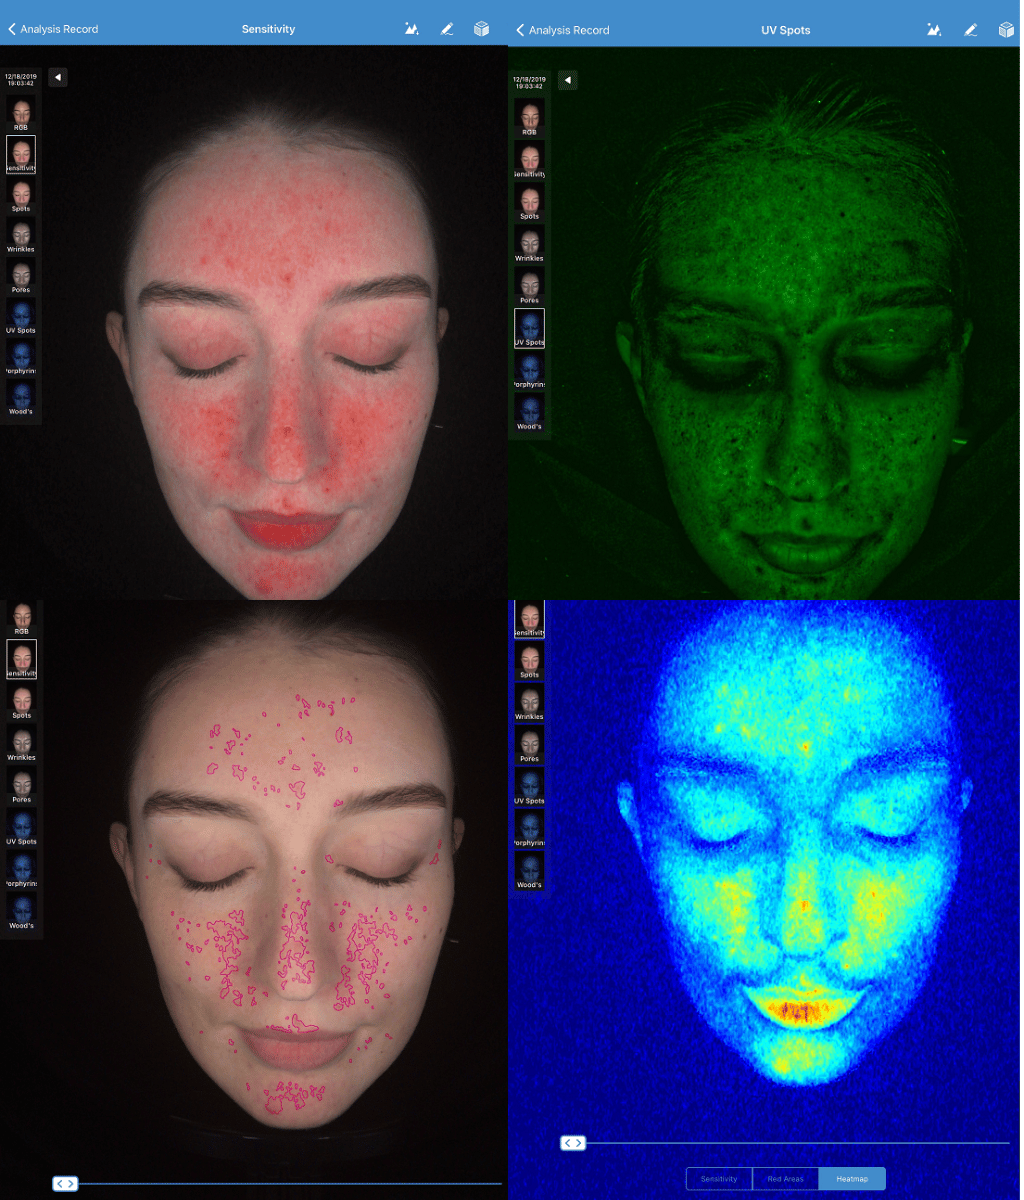
Starts on the skin analysis machine. Your scar types are identified, marks separated from texture, Fitzpatrick skin type recorded, and your history taken — including any isotretinoin, and any tendency to raised scarring. Images are stored. The fee comes off your treatment.
Which scars are treatable here, which are not, how many sessions, over how long, and the total cost including homecare.
The skin is prepared before it is treated, particularly in deeper tones. Skipping this is how treatment causes the marks it was meant to remove.
Sessions four to six weeks apart, adjusted to how your skin responds rather than to a fixed package.
Not against memory. If it has not moved enough, the plan changes or we tell you it has gone as far as it usefully can here.
Collagen keeps remodelling for months after the last session. Maintenance is homecare and sun protection, not an endless course.
Scar treatment is judged in months, not appointments. Here is the honest shape of it, including the parts that are easy to leave out of a sales conversation.
Post-acne redness and pigment are the quickest wins and often improve substantially within a few months, given daily sun protection. If marks are most of your problem, you may need far less than you were expecting.
Collagen remodelling needs repeated treatments spaced four to six weeks apart. Expect a course rather than a session, and expect the plan to be reviewed rather than sold in one go.
New collagen continues to lay down for months after the final treatment, so the honest assessment point is three to six months later, not the week after.
A realistic outcome is a meaningful reduction in how visible the scarring is, particularly in the side lighting that shows it most. Smooth, unmarked skin is not what this buys, whatever the photographs elsewhere suggest.
Two people with the same number of scars get different results depending on the shape of them. That is why the scar type is settled before the plan, and why we will sometimes tell you the money is better spent elsewhere.
Age, skin type, how long the scarring has been there and how deep it goes all change the outcome. You will be given a realistic expectation for your skin, in writing, before you commit.
What you do in the days after treatment affects the result as much as the treatment does, particularly in deeper skin tones where the risk is marking rather than scarring.
Skin is warm, pink and tight after needling, similar to sunburn. Keep it clean and simple: no actives, no exfoliation, nothing fragranced. Water and the aftercare you are given, nothing else.
Redness settles, and after peels the skin flakes. Let it shed on its own — picking flaking skin is how post-treatment marks happen.
Broad-spectrum SPF 50, reapplied. Freshly treated skin marks faster in UV than untreated skin, and that mark can outlast the benefit.
Retinoids and acids go back in when the skin is calm, in the order written on your plan rather than all at once.
Usually the next day after needling, and once flaking has settled after a peel. You are told precisely, before you book.
Leave heat and chlorine for a few days. Heat prolongs redness and chlorinated water irritates a compromised barrier.
Call us if redness worsens rather than settles after 48 hours, if the area becomes painful, or if you develop blistering or a cold sore. None of these is common, and all are easier to manage early.
Do not book a treatment in the week before a wedding, a holiday or anything photographed. Plan around it — we will help you count backwards from the date.
Most people plan treatment around their week rather than taking time off. We will help you pick the dates.
Book your skin consultationDermacy opened in July 2020 and has treated acne, rosacea and pigmentation in the same place ever since. Scarring is the end of that story rather than a separate service, which is why the assessment starts by working out how much of what you see is mark and how much is texture. The clinic was built on fifteen years of hospital experience beforehand, across anaesthesia, pain, oncology, plastic surgery and dermatology.
Anaesthesia, pain, oncology, plastic surgery and dermatology, before the clinic opened in July 2020.
If your scar type needs something we do not offer, you are told at the assessment.
Skin analysis imaging shows how much of what you see is mark and how much is true scarring.
Homecare comes from the same range as the in-clinic protocol, which is why results hold between appointments.
Professional ranges are supplied only to trained clinics and are not the versions sold on the high street. With scarring they matter twice over: what supports the skin between sessions decides how much of each treatment actually holds.
All three are professional cosmetic ranges. None contains a prescription-only medicine, and where your skin genuinely needs one we will say so.
Post-acne marks and scarring behave differently in deeper skin tones, and the risk profile of the treatment changes with them. This gets planned for rather than glossed over.
Your assessment, skin analysis, treatment plan and reviews are carried out within each practitioner’s current professional scope.

Separates marks from true scarring, identifies scar type and skin type, sets the course and the review point, and decides which scarring should be referred rather than treated in clinic.
We also tell you honestly when what you have is mostly marks rather than scars, which is often, and costs far less to put right.
Scarring is the area of skin work where overselling is easiest and most expensive for the person paying. Here is the line.
Scarring treatment is not funded on the NHS, so this is a private decision either way. That is a reason to spend it accurately, not a reason to spend it here.
Most confusion about acne scarring comes from treatments being sold as interchangeable. They are not. This is what each one is for, and where it stops.
| Treatment | What it targets | Typical course | Downtime |
|---|---|---|---|
| Microneedling | Rolling and shallow boxcar scarring, overall texture. Works by triggering collagen remodelling rather than removing tissue. | A course, spaced 4–6 weeks apart, judged at 3–6 months | Redness for a day or two |
| Professional peels | Surface texture, congestion, and post-acne pigment. Supports needling rather than replacing it. | A short course, spaced to tolerance | Flaking for a few days |
| Depigmenting protocols | Brown post-acne marks only. No effect on texture. | Weeks to months, with homecare | Varies with protocol |
| Barrier and anti-inflammatory routines | Red post-acne marks, reactive skin, and preventing new marks. Slow, cheap, and the part most people skip. | Ongoing | None |
| Daily SPF 50 | Stops UV deepening every mark you have. Does nothing for texture and everything for pigment. | Every day, permanently | None |
| Focal and surgical techniquesNot offered here | Ice pick and deep boxcar scars, treated individually rather than resurfaced. | Referred onward | Depends on technique |
| Medical pathwayNot offered here | Raised, hypertrophic and keloid scarring, which resurfacing can worsen. | Referred onward | — |
Two things are worth noticing in that table. Most of what improves post-acne marks costs very little. And the treatments with the biggest price tags are the ones we refer rather than sell.
Scarring is not caused by the spot itself. It is caused by how deep the inflammation went, how long it stayed, and how the skin repaired afterwards. Understanding that explains both what can be improved now and what would have prevented it.
When a blocked pore becomes inflamed and the wall ruptures below the surface, the contents spill into the surrounding skin. The deeper that rupture, the more tissue is involved in the repair.
Repair either loses collagen, leaving a depression — an atrophic scar — or lays down too much, leaving a raised one. Roughly four in five acne scars are the depressed kind.
Narrow, deep inflammation leaves an ice pick scar. Wider destruction with defined edges leaves a boxcar. Tethering beneath the surface pulls the skin down into rolling scars. This is why one person’s scars respond and another’s do not.
Nodules and cysts scar; surface spots usually do not. How long the acne went untreated matters enormously, as does genetics and how the skin heals generally. Picking and squeezing push inflammation deeper and reliably make the outcome worse.
Brown marks are pigment produced during the inflammation. Red marks are vessels that have not yet settled. Neither involves lost collagen, which is exactly why they fade and true scars do not.
Scarring continues to change for around a year after the acne settles, mostly for the better. After that it is stable, and what is left is what treatment works on. Treating too early means treating a moving target; waiting several years does not make it harder.
Every clinical guideline says the same thing: controlling inflammatory acne promptly is the most effective thing anyone can do about scarring, and it costs a fraction of treating the scars afterwards.
Clear answers covering marks and scars, realistic results, sessions, isotretinoin, deeper skin tones, downtime and suitability.
Press a clear glass gently against it. Redness that vanishes under pressure is post-inflammatory erythema, a vessel issue. Colour that stays is post-inflammatory hyperpigmentation, a pigment issue. A dent you can feel, visible in side lighting, is a true scar. The first two fade with time and protection; only the third needs collagen work. We settle this at the assessment before anything is priced.
No. True scars are permanent changes to the skin’s structure, and treatment improves how visible they are rather than erasing them. Marks are different — brown and red post-acne marks genuinely do fade. Anyone promising removal is either talking about marks or not being straight with you.
Enough to change how the skin reads in ordinary light, particularly the side lighting that shows texture most. Rolling scars improve most, shallow boxcar next, ice pick least. You will be given a realistic expectation for your own skin, in writing, at the assessment rather than a percentage borrowed from someone else’s.
Texture work is a course rather than a session, spaced four to six weeks apart, and judged three to six months after the last one because collagen keeps building. The exact number is set once your scar types are known. Marks often need far less than people expect.
Yes, and it is not a delaying tactic. New spots create new marks, so treating scars while acne is active is paying to chase a moving target. It also means resurfacing inflamed skin, which can worsen both pigmentation and scarring. Acne first, then scarring — see acne treatment.
Not during, and not straight after. Isotretinoin changes how the skin heals, so needling and resurfacing wait until you have been off it for a period agreed with your prescriber — commonly six to twelve months. Bring your dates to the assessment and we plan around them. It is worth asking any clinic this before you book.
The pink, red or purple flat marks left where a spot has healed. They are dilated vessels, not pigment and not scarring, and they blanch when pressed. They matter because pigment treatments do nothing for them — a great deal of money gets spent on the wrong target here. They fade over months with protection and barrier repair.
Depth and duration of inflammation mostly. Nodules and cysts scar; surface spots usually do not. Genetics, how long the acne went untreated, and picking all contribute. This is why treating inflammatory acne promptly is the most effective scar prevention there is.
For rolling and shallow boxcar scarring, yes — as a course, with months to remodel. For ice pick scars it largely passes over the problem, because those are narrow and deep and need focal techniques. That difference is why the scar type is settled before a course is sold. See microneedling.
They help surface texture, congestion and the marks left behind, and they support a needling course. They do not lift deep atrophic scarring on their own. We use them where they earn their place and say so where they do not. See chemical peels.
Yes, with the plan built differently. Fitzpatrick IV to VI carry a higher risk of post-inflammatory pigmentation from the treatment itself, and a higher likelihood of raised scarring, so depth and settings are conservative, the skin is prepared first, and sessions are spaced further apart. Being turned away is not the right answer; being treated identically to type II skin is not either.
No. Hypertrophic and keloid scarring is a different condition with a medical pathway, and resurfacing can make it worse. We identify it and tell you where to go. It is more common on the chest, shoulders and jawline, and more common in deeper skin tones.
Generally not. Acne scarring is treated as a cosmetic concern, so it is almost always private. Your GP can still treat active acne, and that is the part worth pursuing on the NHS because it is what prevents further scarring.
Expect redness for a day or two after needling, sometimes a little longer, and flaking after peels. Most people plan treatments around the week rather than taking time off. You are told what to expect before you book.
It is uncomfortable rather than painful, and it is managed. The face is numbed for needling and you will be told exactly what the sensation is like before you agree to anything.
The treated marks do not, but new spots make new marks, which is why acne control and daily sun protection are part of the plan rather than an afterthought. True scarring does not return once improved; it simply does not improve further without more work.
Often yes, once the acne is settled, because the same course can support both. What does not work is treating either while spots are still forming.
It is assessed as its own area. Truncal skin heals more slowly and is the commonest site for raised scarring, so the assessment matters more there, not less.
You are reviewed against your first images rather than against memory. If it has not moved enough, the plan changes, or we tell you it has gone as far as it usefully can here and what the next step would be elsewhere. That conversation happens at review, not after you have bought another course.
Armthorpe, Doncaster, with free customer parking directly outside. Open Monday to Saturday, 10:00 to 20:00, and we see clients from across South Yorkshire — Doncaster, Bawtry, Bessacarr, Rossington, Thorne and Conisbrough among them.
Most people arrive believing they have scarring and leave knowing how much of it is marks that will fade. That answer is worth having before you spend anything. Your consultation starts with a £30 AI skin analysis, completely free when you go ahead with any treatment.
